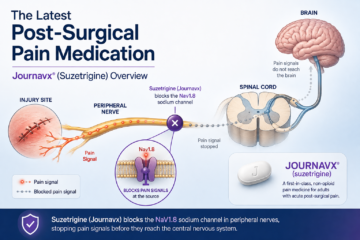
Post-Surgical Pain:
Post-surgical pain is the expected soreness, aching, or throbbing that follows almost every operation as tissues heal. It is usually sharpest in the first 24 to 72 hours and eases over 1 to 2 weeks for most procedures. The modern goal is pain control, not total elimination, using a mix of medications and non-drug strategies.

Table of Contents
TL;DR
- Some pain after surgery is normal and usually peaks in the first 72 hours before steadily improving.
- The safest, most effective approach today is multimodal analgesia: combining acetaminophen, NSAIDs, non-drug strategies, and opioids only when needed.
- Follow your surgeon’s schedule closely, especially in the first 2 to 3 days, and never mix pain medicine with alcohol.
- Red flags include fever, spreading redness, calf swelling, chest pain, shortness of breath, or pain that suddenly worsens.
- If pain is not controlled by your prescribed plan, call your surgical team before doubling up on medication.
What is post-surgical pain?
Post-surgical pain, also called post-operative pain, is the discomfort that arises after any procedure that cuts, stretches, or manipulates body tissues. It is a normal signal that healing is underway, not a sign that something has gone wrong. The clinical aim, according to patient discharge guidance, is to control pain enough that you can breathe deeply, move, sleep, and recover, not to erase every ache.
Almost every operation, from a dental extraction to open-heart surgery, produces some level of pain. What differs is intensity, duration, and the best combination of treatments. For general education and product references, our post-surgical pain resources cover recovery topics in more depth.
Why does surgery cause pain in the first place?
Surgery causes pain because tissue is cut, stretched, or moved, which triggers inflammation and irritates nerves near the surgical site. There are two main types clinicians talk about: nociceptive pain (from tissue injury, often described as aching, throbbing, or sharp) and neuropathic pain (from nerve irritation or injury, often described as burning, tingling, or electric shocks), as summarized in the StatPearls review.
Most post-operative pain starts as nociceptive and settles as inflammation eases. A smaller share becomes neuropathic if nerves near the incision were stretched or irritated. Understanding the type of pain helps your team pick the right medicines, since current guidelines recommend different agents for each.
How long does post-operative pain usually last?
Most post-operative pain is worst in the first 24 to 72 hours, then steadily improves over 1 to 2 weeks, though major joint or bone surgeries can take longer. Minor procedures such as dental extractions often ease within a few days. Larger operations like joint replacements or open abdominal surgery may involve meaningful pain for several weeks, with residual soreness for months.
For hip replacement in particular, patients often describe the first 3 to 5 days as the most intense, followed by rapid improvement once early swelling settles and gentle walking begins. The 2023 acute pain position statement emphasizes that pain plans should extend beyond the hospital, because meaningful discomfort often continues after discharge.
Recovery pain timeline by surgery type
Below is a general education guide only. Your surgeon’s timeline for your specific procedure and health status always takes priority, and healing varies from person to person.
| Procedure | Peak pain window | Typical pain duration | General recovery notes |
|---|---|---|---|
| Dental extraction (simple) | 24 to 48 hours | 3 to 5 days | Ice, soft foods, and scheduled OTC medicines usually work well |
| Laparoscopic abdominal surgery | 24 to 72 hours | 1 to 2 weeks | Shoulder-tip pain from gas is common and self-limiting |
| C-section | 48 to 72 hours | 2 to 6 weeks | Incision soreness eases quickly; deep tissue healing takes longer |
| Foot or ankle surgery | 48 to 72 hours | 2 to 6 weeks | Elevation and multimodal analgesia improve early comfort |
| Hip or knee replacement | 3 to 5 days | 6 to 12 weeks | Early mobilization is uncomfortable but speeds recovery |
| Open abdominal or thoracic surgery | 3 to 5 days | 4 to 8 weeks | Deep breathing exercises reduce lung complications |
What does effective pain management after surgery look like?
Effective pain management after surgery today means multimodal analgesia: combining several treatments that work in different ways so each can be used at a lower dose. Typical building blocks include scheduled acetaminophen, an NSAID when appropriate, a regional block placed by the anesthesiologist, non-drug strategies, and opioids reserved for breakthrough or severe pain, as outlined in the American Pain Society guideline.
Evidence continues to support this approach. A 2022 randomized trial in minimally invasive colorectal surgery showed opioid-sparing multimodal regimens controlled pain as well as morphine-based ones, with fewer side effects. A more recent foot and ankle trial reported better early pain scores and higher patient satisfaction with a structured multimodal protocol.

Common medications used for surgery pain relief
Doctors typically choose from several medication classes, each doing a different job. This is general education, not a prescribing guide. Always take medicines exactly as directed by your surgeon, and see our prescription pain medications catalog for reference on specific products.
| Category | Examples | How it works (in plain terms) | Typical role after surgery |
|---|---|---|---|
| Acetaminophen | Tylenol, paracetamol | Reduces pain signaling in the brain | Scheduled base of most pain plans |
| NSAIDs | Ibuprofen, naproxen, ketorolac | Reduce inflammation at the injury site; ketorolac is a strong injectable/oral NSAID often used short-term | Reduce swelling and lower opioid needs |
| Opioids | Oxycodone, hydromorphone, morphine | Bind to opioid receptors to blunt pain perception | Short courses for moderate to severe pain |
| Gabapentinoids | Gabapentin, pregabalin | Calm overactive nerve signaling by modulating calcium channels | Helpful for nerve-related or neuropathic pain |
| Certain antidepressants | Nortriptyline, duloxetine | Adjust pain-modulating neurotransmitters (serotonin, norepinephrine) | Selected use for persistent neuropathic pain |
| Local anesthetics | Lidocaine, bupivacaine (nerve blocks) | Temporarily numb nerves at the surgical site | Reduce early pain and opioid use |
How do opioids fit into post-surgery pain relief?
Opioids are now reserved for moderate to severe pain that other treatments cannot fully control, and they are usually prescribed as short courses with a plan to taper. Current clinical practice guidelines recommend using the lowest effective dose for the shortest necessary duration, alongside scheduled non-opioid medicines.
That approach reduces side effects (constipation, drowsiness, nausea) and lowers the risk of prolonged use. As comfort improves, most people step down from opioids first, then continue acetaminophen or an NSAID as needed. For deeper reading, our post-operative pain resources cover this in more detail.
Non-drug strategies that actually help pain after surgery
Medication is only part of the plan. Simple, low-risk techniques can noticeably reduce how much pain you feel and how much medicine you need:
- Ice packs for 15 to 20 minutes at a time in the first 48 hours to reduce swelling
- Elevation of the surgical limb above heart level when possible
- Gentle, early movement as approved by your surgeon (short walks, ankle pumps)
- Slow diaphragmatic breathing and guided relaxation to lower muscle tension
- Sleep positioning with pillows to support the surgical area
- TENS units, when recommended, for musculoskeletal pain
- Acupuncture, which the NIH’s NCCIH notes has evidence for post-operative pain, chronic pain, and nausea
These strategies are especially useful in the first two weeks, when pain and stiffness are most active.
How should you take pain medication safely at home?
The safest way to take pain medication at home is to follow your surgeon’s written schedule exactly, stay ahead of pain during the first 48 to 72 hours, and never mix pain medicine with alcohol or other sedatives. Waiting until pain is severe makes it harder to control and often means using more medication overall.
A few practical rules that apply to most home recoveries:
- Take scheduled acetaminophen and any prescribed NSAID on time, even if pain seems manageable
- Use opioids for breakthrough pain and stop them as early as reasonable
- Drink water and eat fiber to reduce opioid-related constipation
- Store medications locked away from children, teens, and visitors
- Dispose of leftover controlled medicines at a drug take-back site
- Call your team before combining new over-the-counter products with prescriptions
These practices are consistent with the American Pain Society guideline and the ANZCA 2023 position statement on safe home recovery.
Who helps manage complicated or long-lasting surgical pain?
Most post-surgical pain is handled by your surgeon and their team, but complicated or persistent pain may involve a physiatrist, a pain management physician, or both. A physiatrist is a physical medicine and rehabilitation doctor who focuses on restoring function through therapy, exercise, and rehabilitation, often after orthopedic or neurologic surgery. A pain management physician specializes in diagnosing and treating pain itself, using medications, injections, nerve blocks, and interventional procedures.
Some patients see both: the physiatrist to rebuild strength and movement, and the pain specialist to address specific pain generators. If pain lasts beyond the expected window for your procedure, ask your surgeon whether a referral makes sense.
What are the warning signs your post-surgical pain isn’t normal?
Warning signs mean the pain may reflect a complication rather than routine healing, and they need prompt medical attention. Per Allina Health’s post-surgery guidance, call your surgeon or seek urgent care for:
- Fever over 101°F (38.3°C) or shaking chills
- Sudden, severe, or rapidly worsening pain
- Spreading redness, warmth, or hardness around the incision
- Foul-smelling or increasing drainage, or the incision opening up
- Calf pain, swelling, or tenderness (possible blood clot)
- Chest pain, shortness of breath, or coughing up blood (call 911)
- Pain that stays severe despite following your medication plan
- Numbness, weakness, or loss of function that is new
Normal recovery pain steadily improves. Pain that suddenly worsens, changes character, or comes with any of the above symptoms is not normal and deserves a call.
Tips to make your recovery easier and less painful
A little preparation goes a long way. Patients who plan ahead tend to report better satisfaction and lower pain scores during the first weeks.
- Set up a recovery space with easy-to-reach water, snacks, chargers, and medications
- Arrange help for the first 48 to 72 hours, especially for meals and transportation
- Prep the fridge with protein, fiber, and hydration in advance
- Fill prescriptions before surgery so you are not waiting in line when you get home
- Keep a simple pain diary (time, pain score, medicine taken, what helped)
- Walk short distances as directed, even when it feels uncomfortable, to reduce clots and stiffness
- Sleep in the position your surgical team recommends, using pillows for support
- Attend every follow-up visit, even if you feel great
Consistency matters more than perfection. Small daily habits, hydration, gentle movement, scheduled medication, add up quickly during the first two weeks.
Frequently asked questions
Is it normal to still have pain two weeks after surgery?
Yes, mild to moderate pain at two weeks is common after many procedures, especially orthopedic, abdominal, or thoracic surgeries. What matters is the trend: pain should be steadily improving, not staying the same or worsening. If pain is intensifying or interfering with sleep and movement, contact your surgical team.
Can I take ibuprofen and acetaminophen together after surgery?
Many surgical teams intentionally combine acetaminophen and an NSAID like ibuprofen because they work through different pathways and provide better pain control together than either alone. However, NSAIDs are not safe for everyone, including some people with kidney disease, ulcers, or specific surgeries where bleeding is a concern. Confirm with your surgeon before combining them.
Why does my pain feel worse at night after surgery?
Pain often feels worse at night because there are fewer distractions, cortisol levels drop, and body positioning can put pressure on the surgical area. Timing your evening dose so it peaks around bedtime, using pillows for support, and keeping the room cool and dark all help. If nighttime pain is severe, mention it at your next follow-up so the schedule can be adjusted.
What should I do if my prescribed pain medicine isn’t working?
Do not double up on doses or add over-the-counter medicines on your own. Call your surgeon’s office and describe the pain: where it is, how intense (0 to 10), what makes it better or worse, and what you have already tried. They can adjust the plan, add a different class of medication, or check for a complication like infection or a blood clot.
When can I stop taking pain medication after surgery?
You can typically taper off pain medication when your pain scores are consistently mild and you can sleep, move, and do daily tasks without significant discomfort. Most people step down from opioids first (often within a few days to a week), then continue acetaminophen or an NSAID as needed. Follow the taper plan your surgical team provides rather than stopping abruptly.